Out-document denials at the bedside
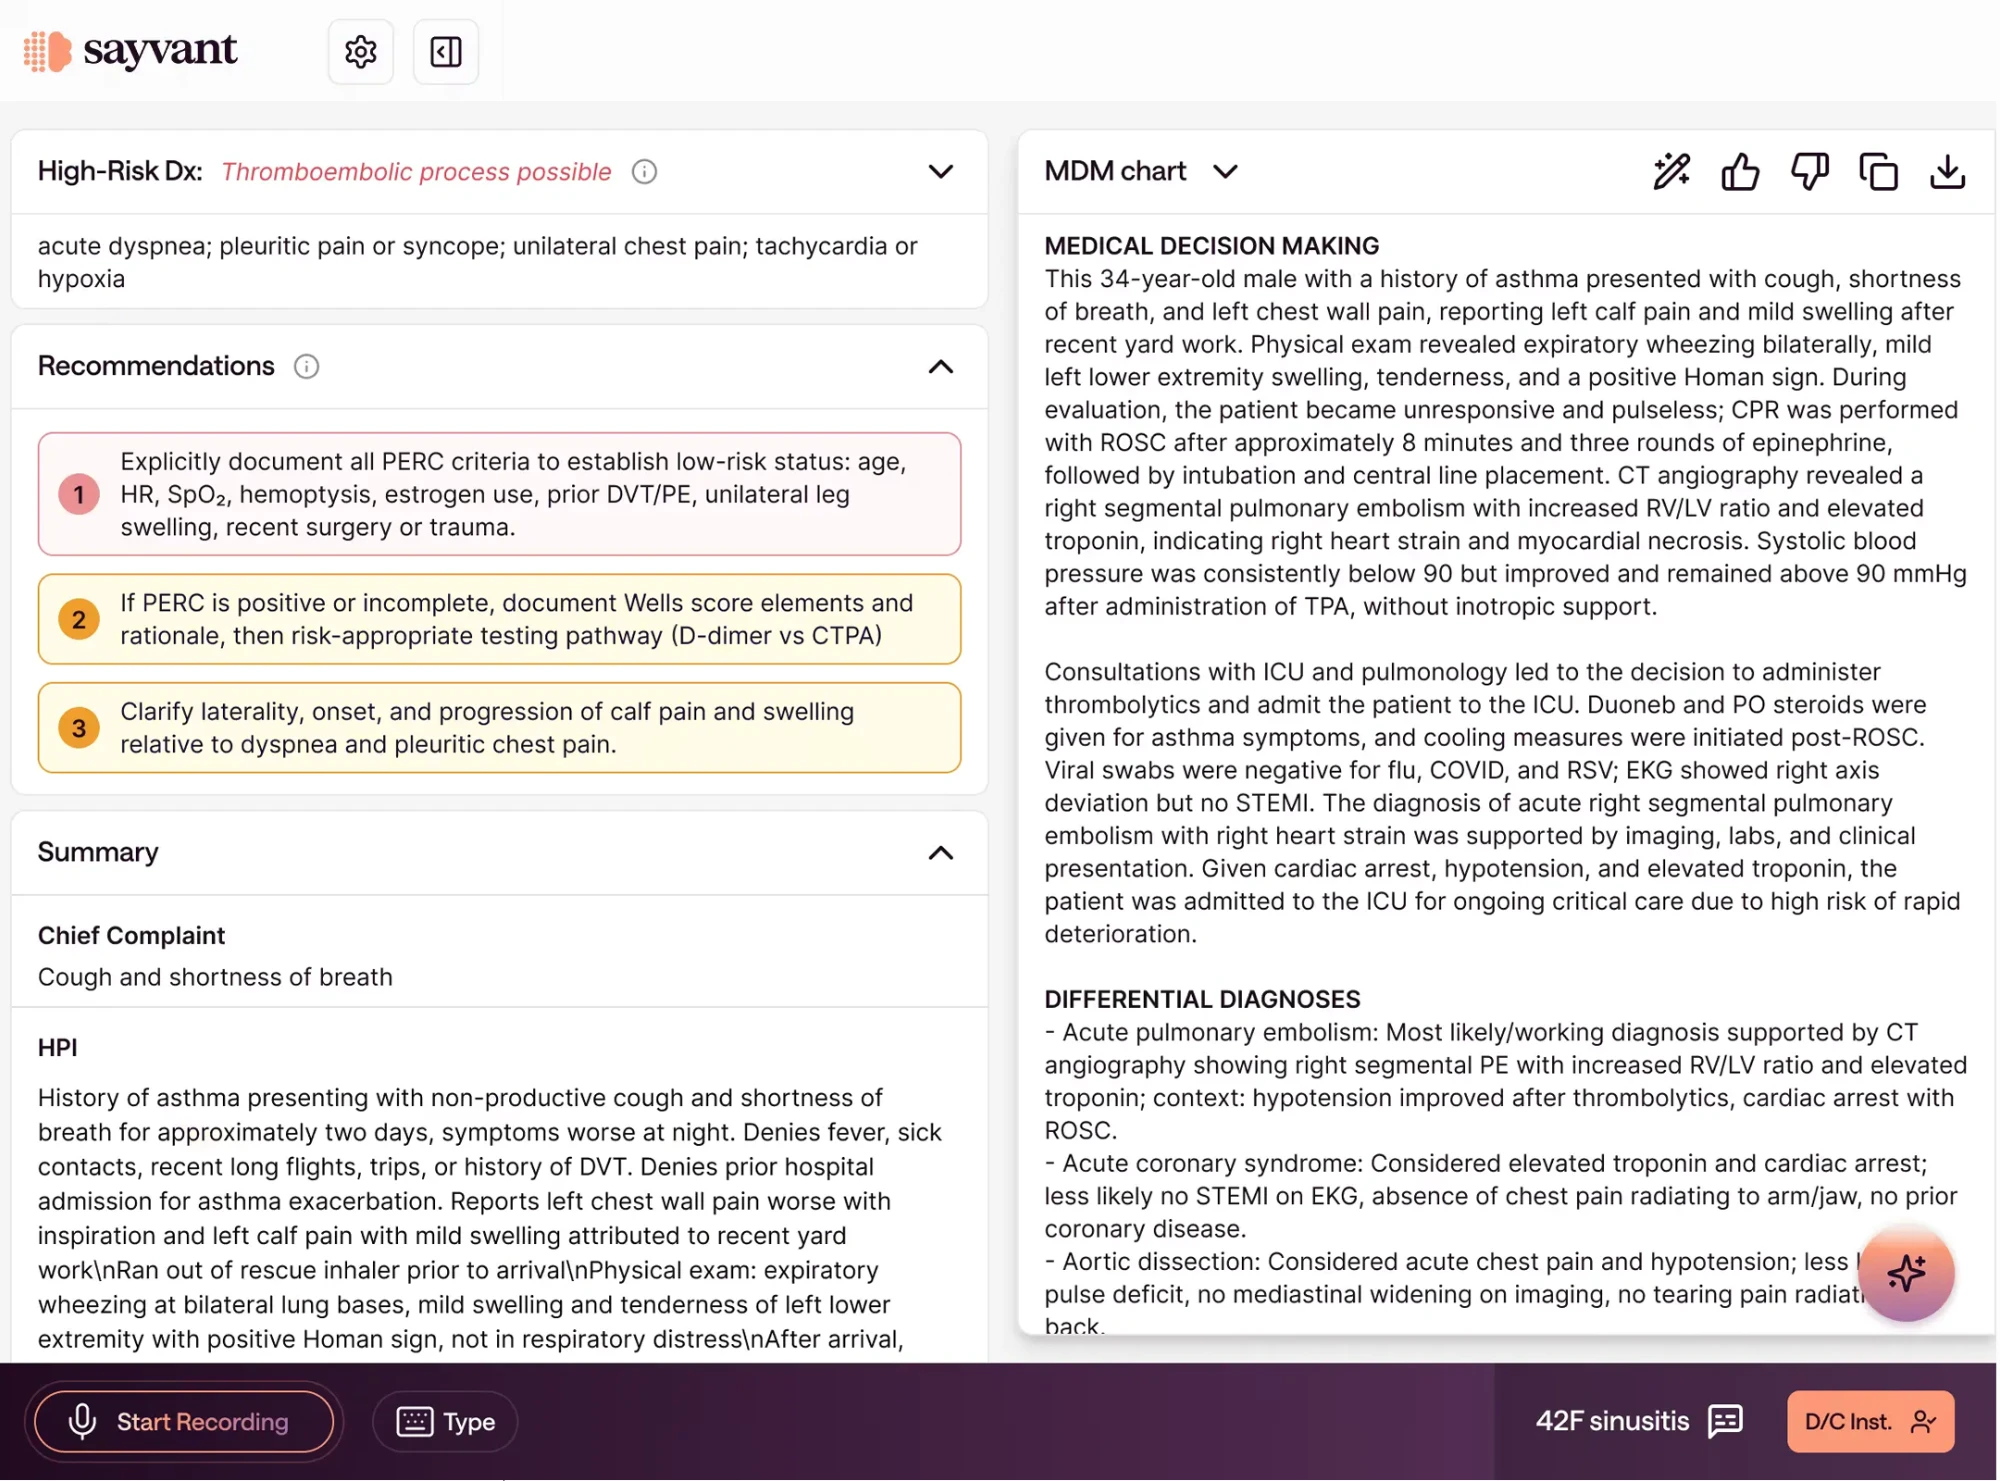
Sayvant drafts the note as the physician works, with medical necessity, complexity and the plan behind every diagnosis already in it. So the chart defends revenue the care earned, before anyone writes a query.
Revenue integrity starts at the point of care
Hospitals increase audits, queries and coding reviews, and denials keep climbing. Because many denials begin long before coding ever touches the chart.
This is no longer just a CDI issue. It is a clinical operations, quality and financial sustainability issue.
The chart is finished before review begins
When documentation doesn't communicate severity of illness, medical necessity and decision-making complexity, the story gets rewritten after discharge.
Retrospective review can't carry the weight
Manual review touches 10 to 20% of charts1. About 18% of CDI programs use any technology to find the denial-vulnerable ones2.
1MDaudit2ACDIS 2025
A query can't add reasoning that was never there
CDI and UR specialists reconstruct clinical intent after the fact, then query a physician who has already moved to the next patient.
Of denials are potentially avoidable
Change Healthcare Denials IndexLost to denials and bad debt in 2025, up 25% in one year
Kodiak, 2,300+ hospital benchmarkOf CDI programs name clinical validation their top denial type
ACDIS 2025 member surveySayvant improves the note where it gets written
Sayvant does the work inside the workflow, in real time, while the clinician is still with the patient — then keeps reading every chart your team never gets to.
Drafts the note as the clinician works
Reasoning, necessity and plan go in from the start, checked against guidelines with evidence cited.
Closes the gap before it becomes a query
Recommendations route to the clinician, judgment calls to CDI and case management. Your team inherits a more complete chart before a query is ever written.
Scales clinical review to 100% of charts
Sayvant Reflect™ reads every chart to flag which denials were preventable, where DRG and medical necessity dollars leak, and how defensibility varies by diagnosis, clinician and facility.
Extend Your Mid-Cycle Capabilities
Point of Care
Highlight improvement opportunities for clinicians in real time, while they're still at the bedside
Pre-Bill Review
Sayvant checks patient status, plan defensibility and complexity before discharge.
Retrospective Analysis
Sayvant Reflect analyzes 100% of settled discharges, benchmarked against peers.
What Sayvant Reflect finds in the charts that never get audited
Inpatient admissions had weak medical necessity documentation
4-hospital community health system, SoutheastCharts missed explicit interpretation of EKGs
Level 2 trauma centerEncounters meeting criteria did not contain critical care documentation
Level 2 trauma center


